

Semaglutide produces more weight loss with far stronger evidence: 15.2% at 2.4 mg weekly over 104 weeks in STEP 5, against about 11% for oral tesofensine 0.5 mg daily over 24 weeks in its Phase 2 trial (9.2 percentage points more than diet plus placebo). Semaglutide is FDA-approved with a 17,604-patient cardiovascular outcomes trial; tesofensine is not approved by any regulator, carries a heart rate and blood pressure signal, and has no multi-year outcomes data. The two compounds are not interchangeable: one is an oral triple monoamine reuptake inhibitor, the other a long-acting GLP-1 receptor agonist. This comparison walks through what the trials actually show and where each compound earns its place.
Key takeaways#
- Semaglutide 2.4 mg weekly produced a 15.2% mean weight reduction at 104 weeks in STEP 5; tesofensine 0.5 mg daily produced 9.2 percentage points more weight loss than diet plus placebo (placebo group: 2.0%) at 24 weeks in TIPO-1.
- Tesofensine is an oral triple monoamine reuptake inhibitor (serotonin, norepinephrine, dopamine); semaglutide is an injectable GLP-1 receptor agonist with a seven-day half-life.
- Tesofensine carries a dose-dependent heart rate and blood pressure signal; semaglutide carries dose-dependent gastrointestinal adverse events (82.2% versus 53.9% on placebo in STEP 5).
- Semaglutide has FDA approval and a 17,604-patient cardiovascular outcomes trial; tesofensine has no FDA approval and no multi-year outcomes data.
- For most adults whose goal is durable weight reduction with documented cardiovascular safety, semaglutide is the better starting point. Tesofensine has a narrower research niche.
How tesofensine works#
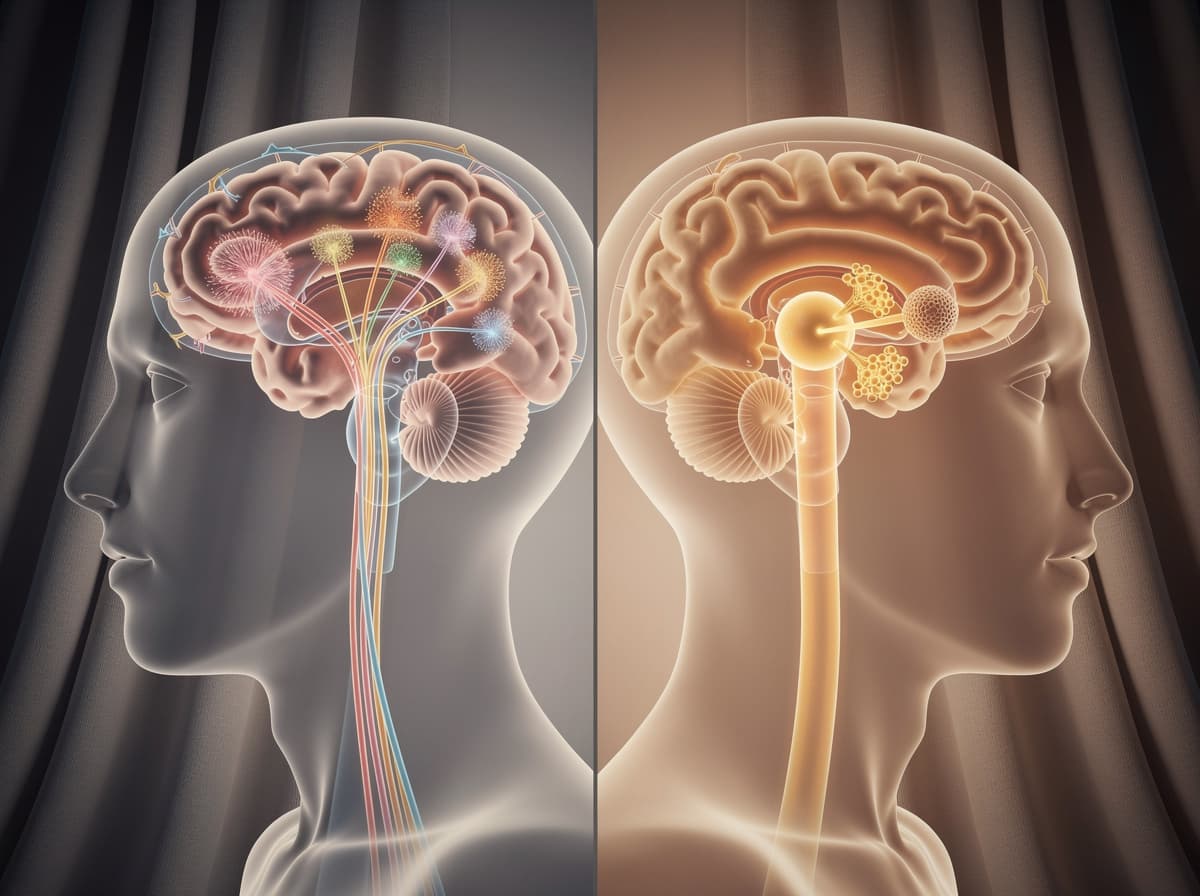
Tesofensine is a small-molecule triple monoamine reuptake inhibitor. It blocks the presynaptic reuptake of serotonin, norepinephrine, and dopamine, raising synaptic concentrations of all three in hypothalamic appetite circuits. The net effect is appetite suppression and increased resting energy expenditure. Pharmacologically, it sits in the same family as nomifensine and sibutramine, both withdrawn for safety reasons, which is why the cardiovascular signal has been the central regulatory question since the compound's first publication.
Originally developed by NeuroSearch for Parkinson's and Alzheimer's disease, tesofensine was repurposed for obesity after researchers noticed unintended weight loss in neurology trials. The compound is orally bioavailable with a half-life of roughly 220 hours, which means once-daily dosing produces stable plasma levels but also a slow washout. Research suggests the long half-life is part of what enables sustained appetite suppression at low milligram doses.
The catch sits in the same mechanism. Sympathomimetic activity at therapeutic doses increases heart rate by up to 8 bpm and blood pressure by 1-5 mmHg at oral doses of 0.25 to 1.0 mg daily. This signal is dose-dependent, and Saniona's own trial documentation says it decided not to develop tesofensine as a stand-alone therapy in the United States or European Union for that reason. A Mexican Phase 3 trial of tesofensine alone, run by Saniona's partner Medix, was completed in 2018, but the resulting application has not been approved: COFEPRIS declined it in November 2024, and Medix resubmitted the dossier in February 2025. Tesomet, Saniona's tesofensine-plus-metoprolol combination, is a separate investigational product aimed at rare eating disorders and is not approved anywhere.
How semaglutide works#
Semaglutide is a long-acting GLP-1 receptor agonist. It mimics endogenous glucagon-like peptide-1, slowing gastric emptying, suppressing glucagon release, augmenting glucose-dependent insulin secretion, and activating hypothalamic satiety circuits. The half-life is approximately seven days, which enables once-weekly subcutaneous dosing at the 2.4 mg obesity dose.
The compound carries several FDA-approved indications across three brand names, Ozempic, Wegovy, and Rybelsus, including type 2 diabetes, chronic weight management, and major adverse cardiovascular event reduction. Wegovy uses a 16-week titration schedule starting at 0.25 mg weekly and escalating to the 2.4 mg maintenance dose. The titration exists to manage gastrointestinal tolerability, which is the main driver of discontinuation.
Mechanistically, the compound is not sympathomimetic. It does not raise heart rate through catecholamine pathways, although a modest 1-4 bpm heart rate increase has been observed across the trial program and is associated with the GLP-1 class effect on autonomic tone rather than direct sympathetic activation. The dominant tolerability problem is gastrointestinal, not cardiovascular.
Dosing: tesofensine vs semaglutide#
Research-published doses for tesofensine in obesity studies typically range from 0.25 mg to 1.0 mg orally once daily, with 0.5 mg as the dose that produced the strongest efficacy-to-tolerability ratio in the TIPO-1 trial. No titration schedule is required. Saniona's investigational Tesomet combination pairs tesofensine with metoprolol to blunt the cardiovascular signal; it has been studied in Phase 2 for rare eating disorders and is not an approved product.
Semaglutide for chronic weight management uses a fixed titration: 0.25 mg weekly for four weeks, then 0.5 mg, then 1.0 mg, then 1.7 mg, then 2.4 mg as the maintenance dose. The 16-week ramp exists specifically to reduce gastrointestinal adverse events. Skipping titration is associated with higher discontinuation rates.
Practical cadence diverges sharply. Tesofensine is taken every morning, orally, on an empty or fed stomach without meaningful pharmacokinetic difference. Semaglutide is injected subcutaneously once weekly, same day each week, with no fasting requirement. For readers tracking adherence friction, the oral daily versus weekly injectable trade-off often matters more than the milligram difference on paper.
Evidence: what the studies actually show#
For semaglutide, the STEP 5 trial randomized 304 adults with obesity (or overweight with comorbidity) to semaglutide 2.4 mg weekly or placebo for 104 weeks. Mean weight change was −15.2% with semaglutide versus −2.6% with placebo, an estimated treatment difference of −12.6 percentage points. 77.1% of the semaglutide group achieved ≥5% weight loss at week 104. The earlier STEP 1 trial at 68 weeks produced 14.9% mean weight loss in 1,961 participants. Cardiovascular outcomes data extends further: the SELECT trial followed 17,604 adults with established cardiovascular disease and obesity for up to four years, showing a 20% reduction in major adverse cardiovascular events versus placebo and sustained weight reduction of −10.2% at 208 weeks.
For tesofensine, the strongest published data is the Phase 2 TIPO-1 trial reported in The Lancet. 203 patients were randomized to tesofensine 0.25, 0.5, or 1.0 mg, or placebo, for 24 weeks. The 0.5 mg dose produced 9.2 percentage points more weight loss than diet plus placebo, with heart rate up 7.4 bpm; the 1.0 mg dose pushed slightly higher (10.6 points). In the 372-patient Phase 3 Viking trial in Mexico, Saniona reported statistically significant weight loss for both doses tested (0.25 and 0.5 mg), an average of about 10% at 24 weeks, with a low incidence of adverse events. The full Phase 3 results have not been published in a peer-reviewed journal. The tesofensine evidence base lacks a multi-year outcomes trial of any kind.
Preliminary evidence from TIPO-4, a 48-week extension, suggested that weight loss was maintained when patients down-titrated from 1.0 mg to 0.5 mg, but the sample was small and unblinded. No equivalent of SELECT exists for tesofensine. This is the single largest asymmetry in the comparison: semaglutide has been shown to reduce hard cardiovascular endpoints, while tesofensine has only been shown to move the scale.

Side effects and contraindications#
The two profiles diverge cleanly. Tesofensine's signal is sympathomimetic: elevated heart rate (mean +5 to +8 bpm at 0.5 mg), elevated blood pressure at higher doses, insomnia, dry mouth, and constipation. Mood disturbance has been reported, which is associated with the dopaminergic component of the mechanism and is the reason patients with active psychiatric conditions were excluded from TIPO-1. Tachyphylaxis to the cardiovascular effect has not been demonstrated.
Semaglutide's signal is gastrointestinal. Nausea, vomiting, constipation, and diarrhea were reported in 82.2% of the STEP 5 semaglutide arm versus 53.9% on placebo, although most events were mild-to-moderate and concentrated in the titration window. Rarer but clinically meaningful concerns include pancreatitis, gallbladder events, and the rodent-derived medullary thyroid carcinoma warning. Studies have shown that the GI signal attenuates over time for most patients but persists as the dominant reason for discontinuation.
Overlap is small. Both compounds reduce appetite. Both produce a modest heart rate increase, although the mechanism and magnitude differ. Neither has been validated in pregnancy, in adolescents under 12, or in patients with severe hepatic impairment.
When to choose tesofensine#
Tesofensine has a narrower defensible use case: research populations where oral daily dosing is preferred over weekly injection; patients who cannot tolerate GLP-1 gastrointestinal effects after a full titration; and contexts where the cardiovascular baseline is well documented and monitored. The compound's appetite-suppressive effect is real and the published data is internally consistent. The research community's interest in tesofensine is also linked to its dopaminergic component, which preliminary evidence suggests may influence reward-driven eating differently than GLP-1 agonism. None of these scenarios make tesofensine a default first-line option.
When to choose semaglutide#
Semaglutide is the better starting point for most adults whose goal is durable weight reduction in the 10-20% range with documented cardiovascular safety. It is the right choice when the patient has type 2 diabetes (where it carries an additional approved indication), established atherosclerotic cardiovascular disease (where SELECT showed event reduction), or a preference for once-weekly dosing. The 16-week titration is a real cost but it is well-characterized, and the long-term maintenance data extends to 208 weeks. For first-time pharmacological weight management, the evidence base is not comparable.
Can you stack them?#
Stacking is not standard practice and is not supported by published data. Mechanistically, the two compounds hit different pathways (monoamine reuptake versus GLP-1 receptor), so a supra-additive effect on appetite is plausible on paper. In practice, the combined autonomic and gastrointestinal load is the problem: stacking a sympathomimetic with a compound that already elevates heart rate modestly creates a cardiovascular profile that has not been studied in any controlled trial. No published study has tested concurrent administration in humans. Anyone considering combined use is operating outside the evidence base entirely.
Verdict#
For the typical adult evaluating pharmacological weight management in 2026, semaglutide is the better starting point. The reason is not nuance: it is magnitude and duration. Semaglutide produces larger mean weight loss (−15.2% at 104 weeks versus roughly −10% to −11% at 24 weeks for tesofensine), with a multi-year outcomes trial showing a 20% reduction in major adverse cardiovascular events, against a tesofensine evidence base that ends at Phase 2 in Europe and a 24-week Phase 3 trial in Mexico, with no long-term outcomes data. Tesofensine has a defensible niche for patients who cannot tolerate GLP-1 receptor agonists after a full titration, but it is not the higher-evidence choice. Earlier marketing language describing tesofensine as producing "double" the weight loss of comparators referenced sibutramine and rimonabant, not modern GLP-1 receptor agonists, and that comparison no longer holds.
Make the decision your health profile actually supports#
The honest answer to "tesofensine or semaglutide" is rarely the same for two readers, because it depends on baseline cardiovascular profile, GLP-1 tolerance, treatment goal magnitude, and whether multi-year outcomes data matters more than oral convenience. Run the Klarovel peptide calculator to see what each compound's research-published dose looks like against your weight and protocol cadence, then complete the intake questionnaire so the protocol layer can map your inputs to the compound the evidence actually points to. The published data, not the marketing, should make the call.
Frequently asked questions
Keep reading
Peptides for Inflammation: Mapping BPC-157, KPV, and Thymosins
Peptides for inflammation compared by mechanism and evidence stage: BPC-157, KPV, thymosin alpha-1, and thymosin beta-4, with FDA status and safety notes.

Mounjaro vs Zepbound: Same Drug, Two Different FDA Labels
Mounjaro and Zepbound are the same drug, tirzepatide, at the same doses. The difference is the FDA label: diabetes for Mounjaro, weight loss for Zepbound.

Rybelsus for Weight Loss: Not Approved, and the Pill That Is
Rybelsus is not FDA-approved for weight loss and moves the scale only a little. The oral semaglutide approved for weight loss is the Wegovy pill at 25 mg.